
Emerging Threats: State Laws Restricting Medication Abortion Access
- Insight
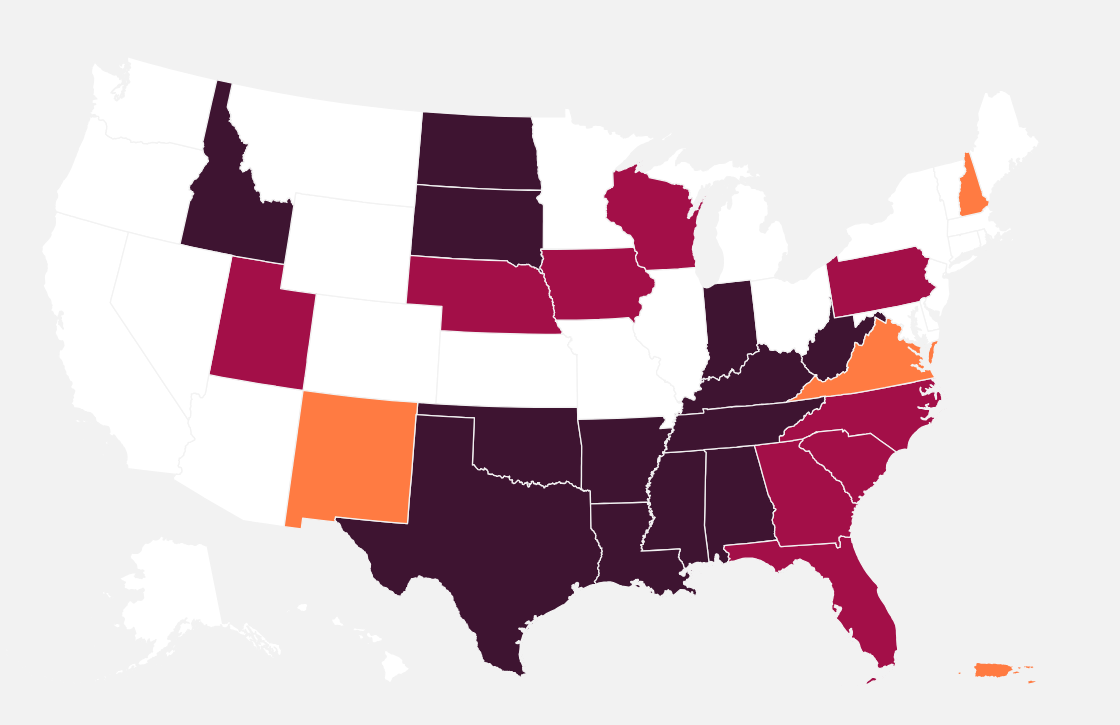
Medication abortion is a lifeline for so many people—and that is exactly why anti-abortion politicians are doing everything they can to prevent people from accessing it.
Medication abortion, particularly access to mifepristone—one of two medications used together in the most common form of medication abortion in the US—remains conclusively at the center of ongoing federal and state policy debates about national abortion access. That’s because medication abortion has become the most common form of pregnancy termination in the US, accounting for over 60% of abortions each year. And in the years since the Supreme Court overturned Roe v. Wade (via the Dobbs decision), there has been a dramatic increase in telemedicine abortion—a process where a patient consults with a licensed healthcare professional online or by phone for a medication abortion prescription. Telemedicine abortions have a high success rate, low risk, and are critical for dismantling the financial and logistical barriers to accessing abortion.
At the federal level, ongoing lawsuits could have significant nation-wide implications for telemedicine abortion (like Louisiana v. Food and Drug Administration (“FDA”), in which Louisiana seeks to re-instate a medically unnecessary in-person dispensing requirement that would require patients throughout the country to travel to a clinic just to pick up their pills). And the Trump FDA is undertaking a politically motivated review of mifepristone, which they may then try to use to justify medically unnecessary restrictions on access, despite FDA’s own findings that mifepristone can be safely dispensed remotely.
State level attacks are equally fierce and equally concerning, as anti-abortion extremists compete to advance a range of experimental attacks on medication abortion, with the ultimate goal of pushing mifepristone even further out of reach.
Increasing penalties for medication abortionIncreasing criminal and civil penalties for medication abortion
Over the past two years, ban state legislators have ramped up their efforts to prohibit the prescribing and mailing of medication abortion into their states in a direct attack on interstate shield laws. These bills target individuals, medical professionals, community networks, and helpers who assist pregnant people in accessing pills.
Anti-abortion legislators remain publicly divided over whether to impose criminal penalties on pregnant people who obtain abortions, a radical position shift with almost zero public support, or to prioritize targeting the providers and others who facilitate access to medication abortion. But even without passing an explicit law criminalizing abortion patients, some states are prosecuting patients for having an abortion anyway. In 2026, Georgia, North Carolina, and Kentucky arrested and prosecuted people for taking medication abortion pills to allegedly end their own pregnancies. Oklahoma, Mississippi, and South Dakota enacted legislation imposing criminal penalties related to facilitating medication abortion access.
States are also targeting healthcare providers, distributors, and even drug manufacturers: six states introduced legislation that would impose criminal penalties for manufacturing, delivering, or prescribing medication abortion.1 Mississippi also enacted a medication abortion “trafficking” bill, adding medication abortion to the state’s list of illegal substances under drug trafficking statutes, which enhances the penalties attached to selling, manufacturing, distributing, prescribing, or possessing with the intent to distribute medication abortion. Together, these laws reflect a broader effort to use criminal law to punish those who provide or facilitate medication abortion, and thus restrict access to care.
At the same time, bills threatening civil liability or “bounty hunter” policies are creating waves across state legislatures. These bills allow private individuals, regardless of their relationship to the pregnant person, to bring civil lawsuits against abortion providers and others who assist with abortion care. For example, in September 2025, Texas enacted House Bill 7 (HB 7). This law incentivizes private citizens to sue anyone alleged to have distributed, provided, or mailed medication abortion into Texas. Just months after its enactment, five states followed suit, introducing similar “bounty hunter” legislation.2 We anticipate that more states with abortion bans will try to follow Texas’s model and expand private enforcement mechanisms targeting people who provide or help others access abortion care.
Medication abortion as a controlled substanceClassifying medication abortion as a controlled substance
Some states are moving new bills that aim to classify mifepristone and other medications as controlled substances. This type of legislation imposes requirements that create barriers to timely access—not only for abortion care, but also other essential medical care. For example, these medications are also used to treat conditions such as post-partum hemorrhage, bleeding from miscarriages, ectopic pregnancies, and rheumatoid arthritis.
Many states maintain their own controlled substance laws that operate alongside the federal Controlled Substance Act. Controlled substances under these laws require special storage, licensing, ordering and documentation procedures to avoid abuse, dependence, or safety risks. Abortion medications do not have the abuse or addiction potential that is associated with controlled substances, which is why (among other reasons) they’ve never been federally designated as such.
Nevertheless, in 2024, Louisiana enacted a law designating mifepristone and misoprostol as controlled substances under state law. These classifications have consequences far beyond abortion access. Evidence from Louisiana shows that the law has already caused patient harm. According to a 2025 report generated by the New Orleans Department of Health, patients experienced delays or were denied access to misoprostol for legal and medically necessary care, including miscarriage management, fertility treatments, IUD insertions, emergency cessation sections, and treatment of postpartum hemorrhages. Clinicians report prescriptions being denied, preventing patients from receiving standard medical treatments. The report also found that the law has hindered emergency care, with providers reporting a ten-minute (or longer) delay in accessing misoprostol during postpartum hemorrhages, a life-threatening condition that can quickly and tragically result in death.
These restrictions subject people who possess or provide these medications to severe criminal penalties, while creating additional barriers to medications that are critical for reproductive and obstetric healthcare. Even when a law does not explicitly criminalize a pregnant person’s possession of abortion medication for personal use, its broad restrictions can create fear and uncertainty. Law enforcement and prosecutors can also interpret or enforce these laws in ways that place abortion seekers, healthcare providers, caregivers and helpers at risk of investigation or prosecution.
Key takeawaysKey takeaways
Medication abortion is a safe, essential healthcare option and a lifeline for people who may not be able to access an abortion clinic in person. It is an important part of ensuring equitable access to care. Everyone should have the freedom to make deeply personal decisions about their bodies, health, and families without government surveillance, interference, or punishment.
Nonetheless, since the Dobbs decision, anti-abortion actors have been pushing increasingly radical attacks on medication abortion that endanger patients’ health and lives. In their single-minded pursuit of eliminating access to abortion, these actors and lawmakers have gone so far as to enable vigilantes to bring bounty-hunter lawsuits against anyone associated with medication abortion, criminalize the mailing of abortion medications, and expand controlled-substance restrictions to essential medications that are used for a wide range of critical health needs—putting lives at risk in the process.
These attacks must be stopped. Punishing patients and medical professionals does not stop them from seeking or providing necessary healthcare. Instead, these attacks only make safe, timely reproductive healthcare harder to access, and put patients’ health and lives in danger.
Citations- Oklahoma, Arizona, Missouri, Mississippi, South Dakota, and West Virginia (H.B. 663 (Fla. 2026), H. 4760 (S.C. 2026), S.B. 173 (W.V. 2026), S.B. 5713 (Wash. 2026), S.B. 599 (W.V. 2026), S.B. 2141 (Miss. 2026), H.B. 812 (Miss. 2026), H.B. 646 (Ky. 2026)). ↩︎
- Florida, South Carolina, West Virginia, Washington, Mississippi, and Kentucky (H.B. 2945 (Okla. 2026), H. 4637 (S.C. 2026), H.B. 118 (Ala. 2026), S.B. 236 (Ind. 2026), S.B. 1657 (Okla. 2026), S.B. 2054 (Okla. 2026), H.B. 2009 (Kan. 2026)). ↩︎
Fuel the Fight for Reproductive Rights
Your donation allows us to defend reproductive rights, change policies, and amplify voices around the globe.